
Why the body fights weight loss, how psychological triggers drive relapse, and why lasting metabolic recovery takes more than willpower.
The patient who tried more than 20 times
He knew the science. He understood calories, insulin, metabolism, nutrition, and the importance of physical activity. He had attempted to correct his weight and metabolic health more than 20 times.
Yet every promising beginning seemed to end in another disappointment.
By the time I saw him, he had accumulated something more damaging than excess body fat: a history of perceived personal failure.
He had experienced bullying at school, difficulties at work, marital conflict, and years of stress. His self-image had deteriorated. He repeatedly described himself as someone who lacked willpower.
But was willpower really the problem?
During our consultation, we explored something that had received far less attention throughout his previous attempts: the psychological landscape surrounding his metabolic condition.
A few months later, he had made a remarkable breakthrough.
His experience raised a question that deserves a central place in modern metabolic medicine:
What if we are asking patients to change their metabolism before preparing their minds to sustain that change?
In my book, Your Metabolic Shift, I devoted a chapter to goal setting because I believe it can become a personal turning point. But clinical experience increasingly suggests that another step may need to come first: understanding the biological, emotional, and behavioural forces that repeatedly pull people back towards old patterns.
To understand why, we must begin with the body itself.
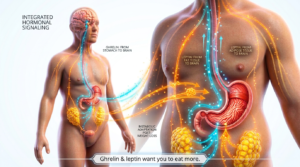
Why the body fights back: the biology of relapse
Imagine your body as a house with a thermostat.
When the temperature drops, the heating switches on automatically. You do not need to make a conscious decision.
Weight regulation has similar feedback systems.
When someone loses substantial weight, the body may interpret the reduction in stored energy as a threat. Several compensatory mechanisms can emerge:
- Ghrelin, the hunger messenger: Often rises following weight loss, increasing the drive to eat.
- Leptin, the energy-reserve messenger: Falls as fat stores decrease, signalling reduced energy availability to the brain.
- Adaptive thermogenesis: Energy expenditure may decline beyond what would be expected from carrying a smaller body, although its magnitude varies considerably.
- Food reward: Foods may become more appealing, and thoughts about eating may become harder to ignore.
These responses are not evidence of poor discipline. They are biological adaptations that can make maintenance difficult.
Again, leptin is not simply a fullness hormone, and ghrelin is not the only hunger hormone. Appetite regulation involves the hypothalamus, brainstem, gut, adipose tissue, and reward circuits, including signals such as GLP-1, PYY, and insulin.
The result is a mismatch: a patient may consciously want to eat less while their biological systems push them to eat more.
The accelerator of hunger may be pressed down just as the patient is trying harder to apply the brakes.
This helps explain why a successful weight-loss programme is not necessarily a successful weight-maintenance programme.
What newer metabolic science tells us
Modern obesity medicine increasingly recognises obesity as a chronic, biologically influenced condition rather than simply the consequence of individual choices.
The evidence from incretin-based medications provides a particularly striking illustration.
In the STEP 1 extension, participants receiving semaglutide had initially lost an average of 17.3% of their body weight. During the year following withdrawal of medication and structured lifestyle support, they regained approximately two-thirds of that lost weight.
In the SURMOUNT-4 trial, participants who stopped tirzepatide regained an average of 14% of their weight measured at treatment withdrawal over the following 52 weeks, while those continuing treatment lost a further 5.5%.
These findings should not be interpreted as proof that everyone needs lifelong medication. They demonstrate something fundamental: removing an effective treatment can expose persistent biological pressures towards weight regain.
A 2026 systematic review further examined regain after stopping GLP-1 and dual GIP/GLP-1 receptor agonists, reinforcing the importance of planning for treatment maintenance and discontinuation.
However, medication does not erase psychological distress, learned coping patterns, or difficult life circumstances.
The most durable approach may therefore require sustained biological treatment, behavioural support, and psychological care working together.
The invisible burden: when repeated attempts damage self-image
Return to my patient.
After more than 20 attempts, his internal conversation had become dominated by self-criticism.
Every relapse reinforced a painful belief: I am the problem.
This is where metabolic difficulties can become entangled with identity.
Weight-related bullying, discrimination, relationship conflict, and repeated disappointment may contribute to shame, anxiety, emotional eating, and avoidance of healthcare.
A person may begin to see their weight not as a health challenge but as evidence of personal inadequacy.
Psychologists call one relevant process internalised weight stigma: accepting negative social stereotypes about body weight and applying them to oneself.
This matters because shame does not reliably produce sustained healthy behaviour. It can instead encourage secrecy, rigid dieting, withdrawal, and a cycle of emotional distress.
The 2026 American Diabetes Association standards specifically recommend exploring experiences of weight stigma, previous treatment attempts, personal goals, and confidence in change during obesity assessment.
We must therefore distinguish two questions:
What metabolic condition does this patient have?
And:
What has living with this condition taught the patient to believe about themselves?
Both deserve clinical attention.

The stimulus-response cycle: why triggers become powerful
Consider a patient returning home after a stressful confrontation at work.
They feel criticised and powerless. When they arrive home, they automatically reach for food, even without substantial physical hunger.
The sequence might look like this:
A simplified emotional eating cycle. Not all lapses involve emotional eating, and the sequence differs from person to person.
Repeated often enough, this becomes a learned response.
The brain discovers that a particular behaviour provides immediate relief, even when the longer-term consequences are unwanted.
The good news is that learned responses can be modified.
Cognitive behavioural therapy (CBT) helps patients identify the connection between situations, thoughts, emotions, and actions. Techniques such as identifying triggers, restructuring unhelpful thoughts, problem-solving, and practising alternative responses can create a pause between stimulus and behaviour.
That pause is an opportunity for choice.
A lapse is not a relapse
This distinction is essential.
A lapse is a temporary departure from an intended behaviour: missing a planned walk, eating beyond one’s intentions, or abandoning a routine for a day.
A relapse is a more sustained return to an earlier pattern that undermines progress.
A lapse does not inevitably become a relapse.
The danger often lies in how you interpret the lapse.
One patient thinks, I had an unplanned meal. I will return to my routine tomorrow.
Another thinks, I’ve ruined everything. I might as well give up.
The second response resembles the abstinence violation effect, a concept from relapse-prevention psychology in which a perceived rule-breaking episode triggers guilt and further disengagement.
Think of a lapse as missing a turn while driving.
You do not abandon the journey because you missed one exit. You adjust the route.
Metabolic care should teach patients to make that adjustment without shame.
Should psychological preparation come before SMART goals?
My answer is yes, as an assessment and preparation process, but not necessarily as a prolonged course that delays treatment.
SMART goals Specific, Measurable, Achievable, Relevant, and Time-bound are valuable. But goals become fragile when the person lacks confidence, emotional support, practical resources, or coping strategies.
Before asking a patient to commit to a target, we should explore what the target means to them.
Are they pursuing health, independence, and improved functioning? Or are they trying to escape shame, rejection, and self-disgust?
The same numerical goal may have very different psychological foundations.
A practical sequence is:
- Understand the story
- Explore previous attempts, stigma, life stress, strengths and barriers.
- Assess readiness and support
Examine confidence, motivation, emotional wellbeing and practical capacity.
- Build coping skills
Practise trigger management, self-compassion, flexible thinking and recovery from lapses.
- Set collaborative SMART goals
Choose achievable behaviours linked to personally meaningful health outcomes.
- Implement, review and adapt
Monitor metabolic health and psychological wellbeing, adjusting support as circumstances change.
This aligns with NICE guidance, which emphasises individual barriers, psychological factors, realistic goals, motivational approaches, and ongoing review.
Crucially, readiness is not a fixed personality trait. It changes with circumstances and support.
Patients do not have to become psychologically perfect before beginning.

How can we identify patients who need intensive preparation?
A universal psychological assessment is valuable, but not everyone needs the same intensity of intervention.
A stepped-care model is more practical.
Every patient could receive a brief, respectful assessment of previous attempts, stress, eating behaviours, confidence, and support.
Patients reporting repeated disengagement, intense self-blame, emotional eating, trauma-related difficulties, significant depression or anxiety, or suspected eating disorders may benefit from more detailed evaluation.
Validated instruments can help, including PHQ-9 for depressive symptoms, GAD-7 for anxiety, and appropriate eating-disorder screening tools. Clinicians must interpret results, not use them as automatic exclusion criteria.
An especially useful question is:
“When things become difficult, what usually happens next?”
The answer may reveal more about relapse vulnerability than another discussion of nutritional knowledge.
A patient with severe distress may need psychological treatment alongside metabolic care. Suspected eating disorders require appropriate specialist assessment before prescribing restrictive interventions.
No single, sufficiently validated score reliably predicts who will relapse or who will benefit most from a preparatory course. Screening should therefore guide additional support, not label patients as weak or unsuitable.
The psychologist’s role: from optional support to integrated care
A psychologist can contribute far beyond motivating someone to follow a diet.
Their role may include assessing emotional and behavioural difficulties, addressing internalised stigma, supporting patients with trauma-related experiences, identifying maladaptive coping patterns, and helping them develop psychological flexibility.
They can also teach relapse-recovery strategies and support family or relationship issues that interfere with treatment.
For a patient whose self-worth depends on weight, this work may be central to sustaining change.
I would strongly advocate psychological literacy across the entire metabolic care team.
Doctors, dietitians, nurses, physiotherapists, exercise professionals, and health coaches should understand motivational interviewing, non-stigmatising communication, basic behavioural principles, and warning signs requiring specialist referral.
This does not mean every professional should practise psychotherapy.
It means every professional should avoid inadvertently reinforcing shame and should know when specialist psychological expertise is needed.
Measuring success: beyond the weighing scales
How do we know whether psychological preparation is working?
Weight change alone cannot answer that question.
A patient may be losing weight while becoming increasingly anxious, rigid, or preoccupied with food.
Another may lose weight more slowly while developing sustainable habits, improved confidence, and better metabolic markers.
A broader evaluation should examine:
- Metabolic outcomes: Weight trajectory, waist measurements, blood pressure, glycaemic control, lipids, and relevant clinical markers.
- Behavioural outcomes: Consistency, flexible self-monitoring, treatment engagement, and recovery speed after lapses.
- Psychological outcomes: Self-efficacy, distress, self-criticism, quality of life, and relationship with food.
The most meaningful question is not simply, Did the patient lose weight?
It is also: Can the patient navigate difficulty without abandoning the process?

Detecting problems early: the relapse-prevention safety net
Relapse prevention should begin at the first consultation, not after significant weight regain.
Regular follow-up provides opportunities to detect changes in sleep, stress, appetite, medication access, emotional wellbeing, and daily routines.
Warning signs may include missed appointments, increasing shame, rigid all-or-nothing thinking, binge-eating symptoms, and withdrawal from supportive relationships.
Respond with curiosity rather than criticism.
Instead of asking: Why have you stopped following the programme?
Ask: What has changed, and what support would help you restart?
A personalised recovery plan might identify predictable high-risk situations, coping alternatives, supportive contacts, and a clear route back into care.
For some patients, this will mean additional behavioural sessions. For others, it may require medication review, treatment of depression, eating-disorder care, or changes to an unrealistic programme.
The objective is not to eliminate every lapse.
It is to prevent an ordinary lapse from becoming a prolonged loss of direction.
If you found this discussion useful, you may be interested in my recently published book, “Your Metabolic Shift”, which explores these concepts in greater depth.
Frequently asked questions
Does repeated weight regain mean my metabolism is permanently damaged?
No. Weight loss can produce persistent adaptations in appetite and energy expenditure, but this does not mean metabolism is permanently damaged. Effective treatment and maintenance strategies can still improve health.
Can psychological therapy prevent weight regain?
It can help address distress, unhelpful thinking, emotional eating, and behavioural difficulties. However, psychological therapy alone cannot guarantee weight maintenance. A 2026 meta-analysis found benefits from several behavioural techniques, including goal setting and self-monitoring, but did not establish a significant overall advantage for preventing post-treatment weight regain.
Should every patient see a psychologist before starting?
Not necessarily. Everyone deserves an assessment of psychological barriers, but specialist involvement should reflect individual needs. Severe distress, suspected eating disorders, and complex trauma-related difficulties particularly warrant assessment.
How do I know whether I am ready?
Ask whether you understand your reasons for change, have a realistic plan, know your likely triggers, and can seek support when difficulties arise. Readiness can be developed during treatment.
What should I do after a lapse?
Avoid compensatory restriction or self-punishment. Identify what happened, return to your usual supportive routines, and consider whether the plan needs adjusting.
The Metabolic Shift: our most important lesson
The science points towards five essential principles: biological adaptations make weight maintenance challenging; psychological distress and stigma can add further obstacles; lapses should be anticipated rather than moralised; preparation and goal setting should be individualised; and long-term success requires ongoing, coordinated care.
My patient’s experience remains a powerful reminder.
For years, he had tried to change his metabolism while carrying the emotional burden of more than 20 unsuccessful attempts.
His breakthrough was not evidence that psychology alone had solved his metabolic condition. It demonstrated the value of finally addressing a dimension of care that had been repeatedly overlooked.
Perhaps the next major advance in metabolic medicine will not come solely from a new drug, dietary formula, or diagnostic test.
Perhaps it will also come from asking a different question at the very beginning:
Before we ask patients to change their bodies, have we helped them develop the understanding, confidence, skills, and support to sustain that change?
Because lasting metabolic recovery is not simply about losing weight.
It is about building a healthier relationship between the body, the brain, and the life a person wants to live.
This article is intended for educational purposes only and should not replace personalised medical advice. Readers with existing medical conditions should consult their healthcare professional before making significant dietary or lifestyle changes.
References
The following include foundational physiological research, randomised clinical trials, systematic reviews, and contemporary clinical guidance.
- Sumithran P, Prendergast LA, Delbridge E, et al. Long-term persistence of hormonal adaptations to weight loss. New England Journal of Medicine. 2011;365(17):1597–1604. DOI.
- Wilding JPH, Batterham RL, Calanna S, et al. Once-weekly semaglutide in adults with overweight or obesity. New England Journal of Medicine. 2021;384:989–1002. DOI.
- Wilding JPH, Batterham RL, Davies M, et al. Weight regain and cardiometabolic effects after withdrawal of semaglutide: The STEP 1 trial extension. Diabetes, Obesity and Metabolism. 2022;24(8):1553–1564. PubMed.
- Aronne LJ, Sattar N, Horn DB, et al. Continued treatment with tirzepatide for maintenance of weight reduction in adults with obesity: The SURMOUNT-4 randomised clinical trial. JAMA. 2024;331(1):38–48. PubMed.
- National Institute for Health and Care Excellence. Overweight and obesity management. NICE guideline NG246. Published 2025; updated January 2026. Clinical guideline.
- American Diabetes Association. Screening, diagnosis, evaluation, and staging of obesity in adults: Standards of Care in Overweight and Obesity—2026. Diabetes, Obesity, and Cardiometabolic CARE. 2026. DOI: 10.2337/doci26-0003. Full text.
- Preuhs K, Eekhout I, Andree R, van Keulen H, van Empelen P. Effective behaviour change techniques for successful weight loss and weight loss maintenance among adults with overweight and obesity: A systematic review and meta-analysis. Obesity Reviews. 2026;27(9):e70195. DOI.
- Mathialagan S, Lau PL, Abdullah HSL. The impact of weightism and weight self-stigma on obese population: A systematic review. SAGE Open. 2025. DOI.
- National Institute for Health and Care Excellence. Evidence review for psychological approaches to address weight stigma in children, young people and adults. NICE Guideline NG246, Evidence Review I. 2025. Full evidence review.
- Rosenbaum M, Leibel RL. Adaptive thermogenesis in humans. International Journal of Obesity. 2010;34(Suppl 1):S47–S55. DOI.



